Serotonin
5-HT
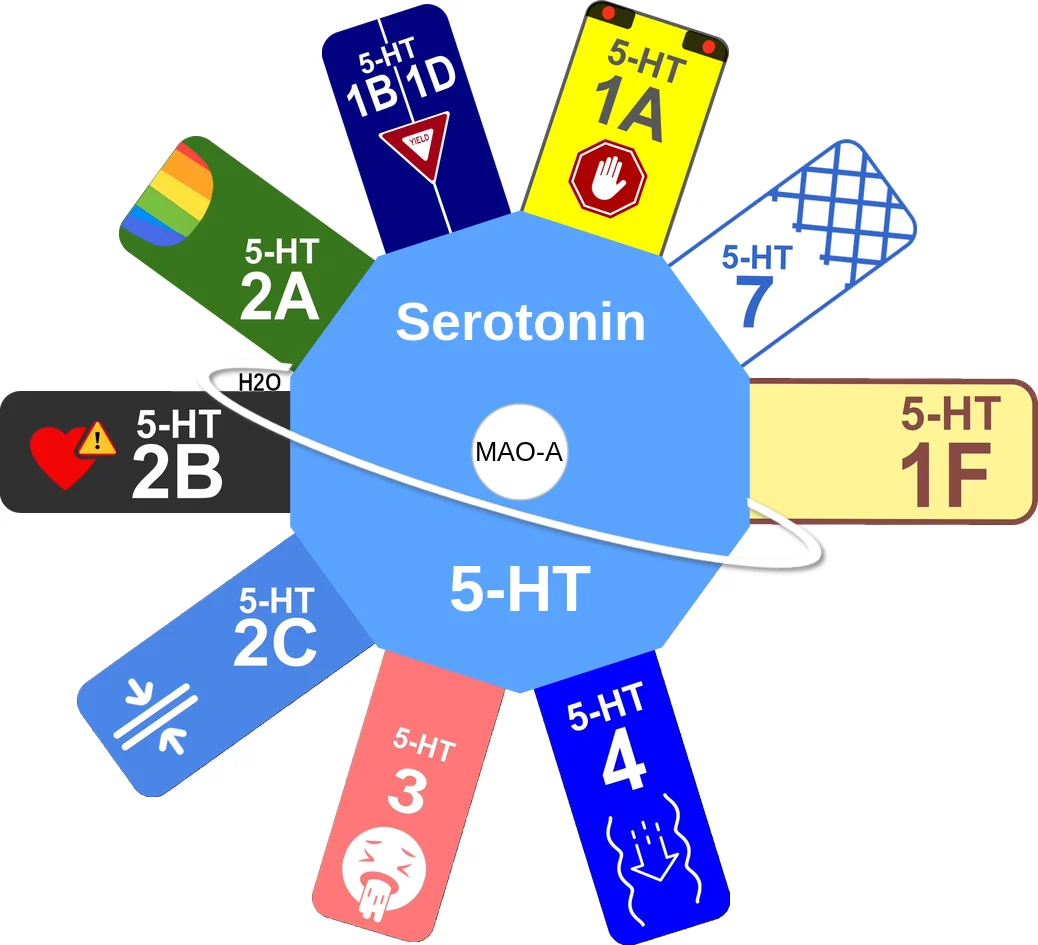
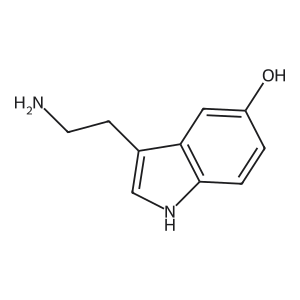
What it isThe endogenous ligand at fourteen receptor subtypes plus SERT.
Why it mattersSerotonicity — how much a drug raises serotonin in the synapse — is the property that drives toxicity; "serotonergic" is vaguer and also covers receptor blockers that raise nothing.
What it changesIt does not cross the blood-brain barrier, so peripheral and central serotonin are effectively separate systems.
NO BOXED WARNINGS
Principal riskEndogenous or dietary; no boxed warning applies
Serotonicity
Serotonicity: how much a drug raises serotonin in the synapse — or why it does not.
Why we needed a new word
- “Serotonergic” is vague — it covers receptor blockers too
- Mirtazapine and trazodone are called serotonergic; neither raises serotonin
- Sumatriptan is a serotonin agonist with no serotonin elevation
- Serotonicity names the one property that drives toxicity
Three ways up
The only mechanisms that raise synaptic serotonin
- Block reuptake — SERT inhibition
- Block breakdown — MAO-A inhibition
- Force release — the transporter run in reverse
- Precursor loading adds substrate: tryptophan, 5-HTP
Everything else acts downstream, on serotonin already released
What it is not
Receptor action is not elevation.
- 5-HT2A antagonists — trazodone, mirtazapine, olanzapine: protective
- 5-HT1B/1D agonists — triptans: no meaningful SERT affinity
- 5-HT3 antagonists — ondansetron: blockade is the opposite of the problem
- 5-HT1A partial agonists — buspirone
All four are routinely withheld out of a fear the evidence does not support
Mirtazapine
The class name says “specific serotonergic”. The serotonicity is zero.
Noradrenergic and specific serotonergic antidepressant (NaSSA)
- No reuptake inhibition, no MAO inhibition, no release
- Does not cause serotonin toxicity with an MAOI
- No sexual side effects — those are serotonin-mediated, and absent
- Not effective in OCD
- Its most potent action is H1 antagonism
Four human tests
Gillman: how to tell real serotonicity from a binding number
- Retarded orgasm
- Efficacy in OCD and cataplexy
- Clonus and hyperreflexia in single-drug overdose
- Serotonin toxicity when combined with an MAOI
A measurable SERT affinity that fails all four is not clinical serotonicity
Why it takes two
Severe serotonin toxicity needs two mechanisms, not one.
- SRI + MAO-A inhibitor — the combination that kills
- Two SRIs together — additive side effects, rarely toxicity
- Releaser + MAOI — a pressor crisis, not serotonin toxicity
- 5-HT2A antagonism mitigates — which is why cyproheptadine and chlorpromazine treat it
Related
The rest of the topic
- Serotonin reuptake inhibitor — what is and is not an SRI
- MAO-A inhibitor — what counts as a relevant MAOI
- Serotonin releaser — pressor response vs toxicity
- 5-HT2A antagonist — mitigation, and the treatment