Amitriptyline
ELAVIL
Pronunciation: a-mee-TRIP-ti-leen
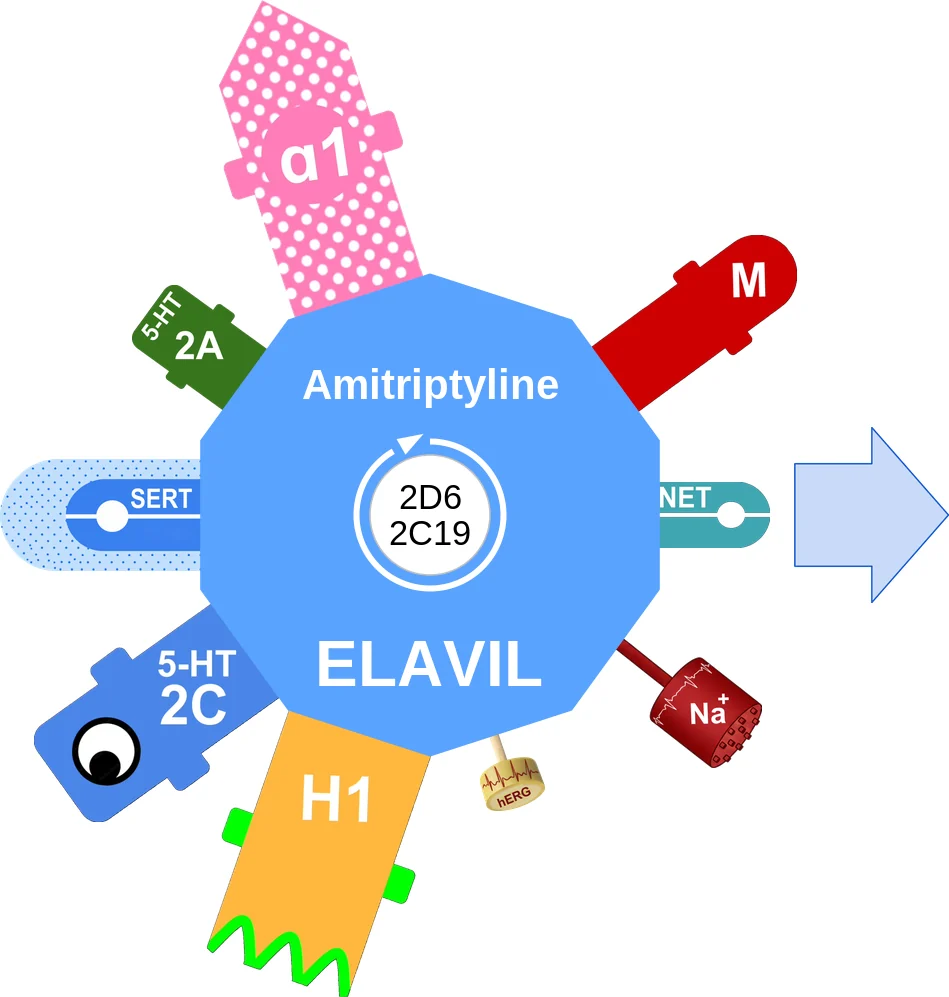

“Amy tripping off the Elevator”
Polka dots on pink → α1 blocker → syncope if titrated too quickly (hit the floor)
“Red as a beet” crimson color theme → anticholinergic
Crown → antihistamine
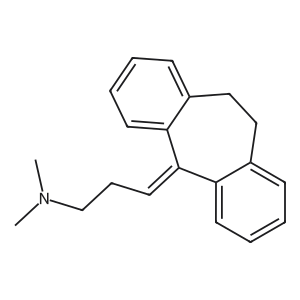
What it isTricyclic serotonin and norepinephrine reuptake inhibitor with broad receptor blockade; depression, pain, migraine and insomnia.
Why this oneAmong TCAs it is especially sedating and antimuscarinic, making bedtime use practical but tolerability worse than nortriptyline.
What limits itAntimuscarinic burden, orthostasis and sedation make it poor for older adults; sodium-channel blockade makes overdose rapidly lethal.
FDA-approved for
- depression (~1961)
Off-label
- neuropathic pain
- migraine prophylaxis
- insomnia
- IBS
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Depression | Adult outpatient | 75 mg/day divided (or 50–100 mg QHS) | 50–100 mg/day | 150 mg/day |
| Depression | Adult hospitalized | 100 mg/day | — | 200–300 mg/day |
| Depression | Adolescent/elderly | 10 mg TID + 20 mg QHS | — | — |
Renal Undefined
Hepatic Undefined
Instructions
- Initiate low and increase gradually; maintenance may be given as a single bedtime dose.
- Taper gradually to discontinue (abrupt cessation may cause nausea, headache, malaise).
- Allow ≥14 days after stopping an MAOI before starting; not recommended during acute post-MI recovery.
Available strengths
- tab 10, 25, 50, 75, 100, 150 mg
Contraindications
- MAOIs (concurrently or within 14 days) due to risk of hyperpyretic crises, severe convulsions, and death
- Concomitant cisapride (increased QT interval and arrhythmia risk)
- Acute recovery phase following myocardial infarction (not recommended)
Cautions
- Suicidality (see Boxed Warning)
- Anticholinergic effects (urinary retention, increased ocular pressure, paralytic ileus)
- Cardiovascular (arrhythmias, orthostatic hypotension, MI, conduction changes)
- Seizures
- SIADH/hyponatremia
- Neuroleptic malignant syndrome and serotonin syndrome reported
- Withdrawal symptoms on abrupt cessation
Adverse reactions
- Drowsiness
- Dizziness
- Dry mouth
- Constipation
- Blurred vision
- Urinary retention
- Orthostatic hypotension
- Tachycardia/palpitations
- Weight gain
- Arrhythmias
Pregnancy No adequate human studies; crosses the placenta with rare reports of CNS effects/limb deformities—use only if benefit justifies risk.
Lactation Undefined
Cost
Generic entry1982
⚠ BOXED WARNING
- Suicidal thoughts and behaviors in patients under 25
Classes and tags
Clinical profile
Legacy pregnancy categoryC
Defining liabilityAnticholinergic effects and cardiac sodium-channel blockade make overdose rapidly life-threatening.
Serotonicity
This drug is routinely called serotonergic. By Gillman’s human-effect criteria it does not raise serotonin in the synapse.
Gillman: SERT binding too weak to cause serotonin toxicity at therapeutic doses, even with an MAOI. The label still contraindicates MAOIs (concurrently or within 14 days).
It binds the serotonin transporter, and its SERT peg is drawn to that textbook affinity. The pale halo around the peg marks binding that, by Gillman’s human-effect criteria, does not produce clinical serotonin reuptake inhibition. Its SERT Ki of 4.3 nM is stronger than its NET Ki of 35 nM, and the pegs keep that textbook order; the halo is what says the SERT binding does not behave like an SRI’s.
Gillman’s four human testsA measurable SERT affinity that fails all four is not clinical serotonicity.
- Retarded orgasm
- Efficacy in OCD and cataplexy
- Clonus and hyperreflexia in single-drug overdose
- Serotonin toxicity when combined with an MAOI
Non-elevating action5-HT2A antagonism may be present
Evidence confidenceHigh
Background: what serotonicity is · what is and is not an SRI · what counts as a relevant MAOI.
Active metabolites
Open Amitriptyline in the interactive console ↗

