Valproate sodium IV
DEPACON

“Dipsy”
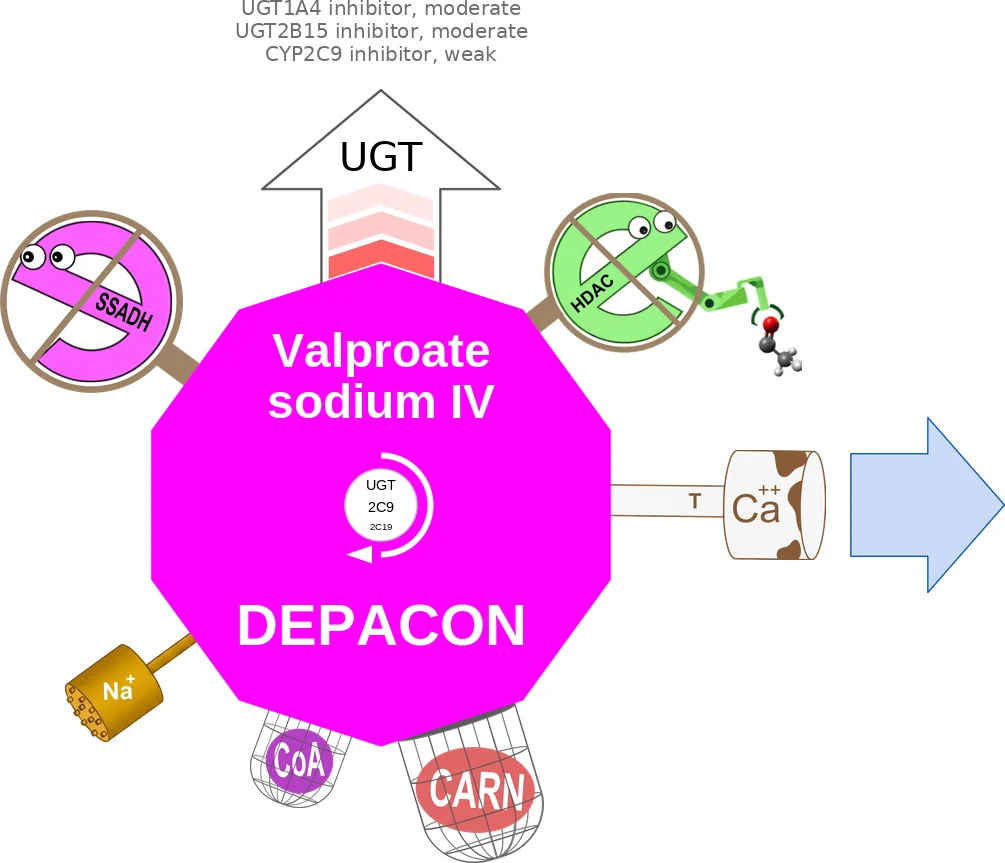
UGT inhibitor
Major teratogen
What it isIV sodium- and T-type calcium-channel anticonvulsant for seizures and temporary oral-valproate replacement (DEPACON); approved 1996.
Why this oneConverts 1:1 — same total daily dose, same dosing frequency, infused over 60 minutes.
What limits itAn oral-replacement label, not an emergency loading label; hepatotoxicity, pancreatitis, hyperammonemia, and thrombocytopenia matter. Avoid in pregnancy and mitochondrial disease.
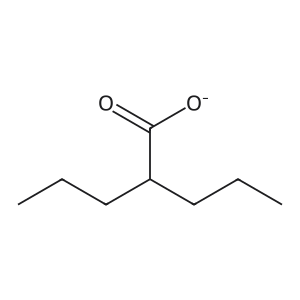
FDA-approved for
- seizures (1996)
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Complex partial seizures (mono- & adjunctive) — IV alternative when oral temporarily not feasible | Adults & peds >=10 yr | 10-15 mg/kg/day IV (60-min infusion, <=20 mg/min) | Titrate to response; usual <60 mg/kg/day (plasma 50-100 mcg/mL) | 60 mg/kg/day |
| Simple & complex absence seizures (sole & adjunctive) — IV alternative when oral temporarily not feasible | All ages studied | 15 mg/kg/day IV (60-min infusion, <=20 mg/min) | Titrate until seizures controlled or limiting side effects (plasma 50-100 mcg/mL) | 60 mg/kg/day |
Titration Increase by 5-10 mg/kg/day at 1-week intervals
Renal Undefined
Hepatic Contraindicated in hepatic disease or significant hepatic dysfunction
Monitor more closely near 60 mg/kg/day, particularly without enzyme-inducing co-medication.
Instructions
- IV use only; infuse over 60 min at <=20 mg/min; dilute in >=50 mL compatible diluent (D5W, NS, LR — stable 24 h); discard unused vial contents
- Use beyond 14 days not studied — switch to oral valproate as soon as clinically feasible
- Replacement of oral therapy: same total daily dose and same frequency as oral product; monitor levels — with BID/TID IV dosing trough equivalence unproven (steady-state equivalence shown only q6h), monitor troughs closely
- Rapid infusion increases adverse reactions; single infusions up to 15 mg/kg over 5-10 min (1.5-3 mg/kg/min) were generally well tolerated in one safety study
- If total daily dose >250 mg, give in divided regimen
- Do not discontinue abruptly when preventing major seizures — risk of status epilepticus
- Conversion to monotherapy: reduce concomitant AED ~25% every 2 weeks
- Elderly: reduce starting dose, increase more slowly; monitor fluid/nutrition, somnolence
- On rufinamide: start valproate low and titrate to effect
Available strengths
- inj 100 mg/mL
Contraindications
- Hepatic disease or significant hepatic dysfunction
- Mitochondrial disorders caused by POLG mutations (e.g., Alpers-Huttenlocher); children <2 yr with suspected POLG-related disorder
- Urea cycle disorders
- Migraine prophylaxis: pregnancy, or childbearing potential without effective contraception
Cautions
- Hepatotoxicity, incl. fatal — monitor serum liver tests before and frequently during therapy (esp. first 6 mo); age <2 yr, polytherapy, metabolic/organic brain disease at highest risk
- Fetal risk: neural tube defects, major malformations, decreased IQ/neurodevelopmental disorders — avoid in women of childbearing potential unless other options failed; effective contraception + folate
- Pancreatitis, incl. fatal hemorrhagic — discontinue if diagnosed
- Hyperammonemic encephalopathy (evaluate for urea cycle disorders; risk increased with concomitant topiramate) — measure ammonia if unexplained lethargy/vomiting/mental-status change; hypothermia can co-occur
- Dose-related thrombocytopenia, coagulation abnormalities (low fibrinogen, acquired von Willebrand) — CBC + coags at baseline, periodically, before surgery, and in pregnancy
- Hypothermia (<35 C), with or without hyperammonemia
- DRESS/multiorgan hypersensitivity — discontinue
- Somnolence in the elderly — reduce starting dose, titrate slowly, monitor intake/dehydration
- Post-traumatic seizure prophylaxis: higher death rate with IV valproate vs IV phenytoin (13% vs 8.5%) in acute head-injury trial
Adverse reactions
- IV-specific: dizziness and injection-site pain (more frequent at faster infusion rates), injection-site reaction, taste perversion; discontinuations for nausea/vomiting and elevated amylase
- Plus all adverse reactions of oral valproate: nausea, somnolence, tremor, thrombocytopenia, alopecia, weight change, hyperammonemia
Pregnancy High teratogenicity: neural tube defects ~1-2% (registry major-malformation rate 9-11% at ~1,000 mg/day), craniofacial/cardiac/limb defects, hypospadias; decreased IQ, ASD/ID/ADHD risk; dose-dependent, no safe threshold. Contraindicated for migraine prophylaxis; epilepsy/bipolar only if other drugs failed. Do not stop abruptly (status epilepticus). Folate + NAAED registry (1-888-233-2334).
Lactation Excreted in milk at 1-10% of maternal serum levels (infant serum 0.7-4 mcg/mL, 1-6% of maternal); no adverse developmental/cognitive effects reported through age 6. Monitor breastfed infant for jaundice and unusual bruising/bleeding (hepatic failure and clotting abnormalities reported in valproate-exposed offspring).
Cost
| Strength | #/mo | generic $/unit | CostPlus | |
|---|---|---|---|---|
| 100 mg/mL | inj | per unit | not offered |
⚠ BOXED WARNINGS
- Hepatotoxicity
- Fetal risk including neural tube defects and reduced IQ
- Pancreatitis