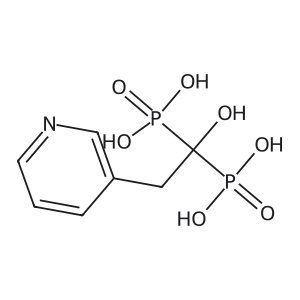
Risedronate
ACTONEL
Pronunciation: ris-ED-roe-nayt (AK-toe-nel)
What it isBisphosphonate inhibiting osteoclasts; osteoporosis.
Why this oneIt reduces both vertebral and hip fracture, and the delayed-release form can be taken after breakfast.
What limits itEsophagitis precautions as for the class. Avoid below eGFR 30; consider a drug holiday after five years.
FDA-approved for
- osteoporosis (2000)
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Postmenopausal osteoporosis — treatment | Postmenopausal women | 5 mg QD, or 35 mg once weekly, or 75 mg on 2 consecutive days once monthly, or 150 mg once monthly | ||
| Postmenopausal osteoporosis — prevention | Postmenopausal women | 5 mg QD or 35 mg once weekly (75 mg on 2 consecutive days/month or 150 mg once monthly may be considered) | ||
| Osteoporosis in men — increase bone mass | Men | 35 mg once weekly | ||
| Glucocorticoid-induced osteoporosis — treatment and prevention | Men & women on ≥7.5 mg/day prednisone equivalent | 5 mg QD | ||
| Paget's disease of bone | Men & women | 30 mg QD × 2 months |
Renal Not recommended if creatinine clearance <30 mL/min (lack of clinical experience); no dosage adjustment needed if CrCl ≥30 mL/min.
Hepatic No dosage adjustment needed (not hepatically metabolized).
Missed-dose limits: do not take more than two 75 mg tablets, or more than one 150 mg tablet, within 7 days.
Instructions
- Swallow tablet whole with 6–8 oz plain water at least 30 minutes before the first food, drink, or other medication of the day
- Do not lie down for 30 minutes after taking
- Do not chew or suck the tablet (oropharyngeal ulceration risk)
- Take supplemental calcium and vitamin D if dietary intake is inadequate, at a different time of day
- Correct hypocalcemia and disturbances of bone/mineral metabolism before starting
Available strengths
- tab 5, 30, 35, 75, 150 mg
- DR tab 35 mg
Contraindications
- Abnormalities of the esophagus that delay esophageal emptying (e.g., stricture or achalasia)
- Inability to stand or sit upright for at least 30 minutes
- Hypocalcemia
Cautions
- Upper GI adverse reactions (esophagitis, esophageal ulcers/erosions) — discontinue and evaluate if dysphagia, odynophagia, retrosternal pain, or new/worsening heartburn
- Hypocalcemia must be corrected before starting
- Osteonecrosis of the jaw
- Severe, sometimes incapacitating bone, joint, and/or muscle pain — discontinue if severe
- Atypical low-energy femoral shaft fractures — evaluate new thigh/groin pain
- Not recommended in severe renal impairment (CrCl <30 mL/min)
- Ascertain and address sex-steroid hormonal status before treating glucocorticoid-induced osteoporosis
Adverse reactions
- Back pain, arthralgia (>10%)
- Abdominal pain, dyspepsia (>10%)
- Diarrhea, nausea, constipation
- Rare hypersensitivity/skin reactions (angioedema, generalized rash, bullous reactions, Stevens-Johnson syndrome, toxic epidermal necrolysis)
- Eye inflammation (iritis, uveitis) — rare
- Acute phase reactions (flu-like symptoms)
Pregnancy Available data insufficient; discontinue when pregnancy is recognized. Potential for fetal skeletal harm because bisphosphonate is retained in bone.
Lactation No human milk data; small lacteal transfer seen in rats; weigh maternal need against potential infant risk.
Cost
Generic entry2007
NO BOXED WARNINGS
Principal riskEsophagitis; remain upright
Classes and tags
Clinical profile
Legacy pregnancy categoryC
Defining liabilityGenerally tolerated at therapeutic doses; clinically important risks are agent-specific and increase with interactions or organ impairment.