Nirmatrelvir
in PAXLOVID

“Normal traveler”
What it isSARS-CoV-2 main protease inhibitor, given with ritonavir; early COVID-19 in those at risk of progression.
Why this oneSubstantial reduction in hospitalization when started within five days of symptom onset.
What limits itThe ritonavir booster is the problem: it is a strong CYP3A4 inhibitor, so statins, some anticoagulants and many other drugs must be held. Renally adjusted.
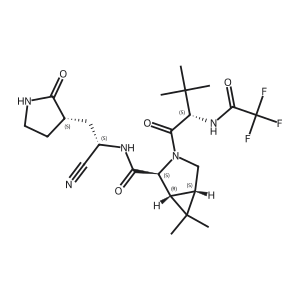
FDA-approved for
- COVID-19 (2023)
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Mild-to-moderate COVID-19 at high risk of progression to severe disease | adult | 300 mg nirmatrelvir + 100 mg ritonavir BID × 5 days | 300 mg/100 mg BID × 5 days |
Renal Moderate (eGFR 30–<60): 150 mg/100 mg BID; severe (<30, incl. hemodialysis): 300/100 once Day 1 then 150/100 QD Days 2–5; no adjustment if mild
Hepatic Not recommended in severe (Child-Pugh C); no adjustment for mild–moderate
Complete the full 5-day course
Instructions
- Start as soon as possible after diagnosis and within 5 days of symptom onset
- Take all 3 tablets together twice daily for 5 days, with or without food
- Swallow whole; do not chew, break, or crush
- Nirmatrelvir must always be co-administered with ritonavir
- On hemodialysis days, dose after dialysis
Available strengths
- tab 150 mg
Contraindications
- History of clinically significant hypersensitivity (e.g., TEN, SJS) to nirmatrelvir, ritonavir, or components
- Co-administration with CYP3A substrates where elevated levels cause serious/life-threatening reactions (e.g., alfuzosin, amiodarone, dronedarone, colchicine, lurasidone, pimozide, ergot derivatives, lovastatin/simvastatin, oral midazolam, triazolam, sildenafil for PAH)
- Co-administration with strong CYP3A inducers (e.g., rifampin, carbamazepine, phenobarbital, phenytoin, St. John's Wort, apalutamide, enzalutamide)
Cautions
- Serious/life-threatening reactions from drug interactions (e.g., calcineurin inhibitors, calcium channel blockers)
- Hypersensitivity/anaphylaxis, SJS/TEN
- Hepatotoxicity (ritonavir)
- Risk of HIV-1 resistance in uncontrolled/undiagnosed HIV-1
Adverse reactions
- Dysgeusia
- Diarrhea
- Headache
- Hypertension
- Nausea/vomiting
- Abdominal pain
Pregnancy Human data insufficient; ritonavir observational data show no increased birth-defect risk
Lactation Present in breast milk in small amounts (<2%); weigh benefits and risks
Cost
| Strength | #/mo | generic $/mo | CostPlus | |
|---|---|---|---|---|
| 150 mg | tab | 60 BID | not offered |
Available combined with: nirmatrelvir / ritonavir
⚠ BOXED WARNING
- Significant drug interactions
Principal riskThe ritonavir booster’s CYP3A4 interactions
Classes and tags
Clinical profile
Open Nirmatrelvir in the interactive console ↗
Memory aids: interaction avatars
