Leucovorin
WELLCOVORIN
Pronunciation: loo-koe-VOR-in
What it isReduced folate bypassing dihydrofolate reductase; methotrexate rescue and fluorouracil potentiation.
Why this oneIt rescues normal cells from methotrexate yet paradoxically strengthens fluorouracil's antitumor effect.
What limits it⚑ Rescue must start on time; delay makes it ineffective. It does not correct renal methotrexate retention.
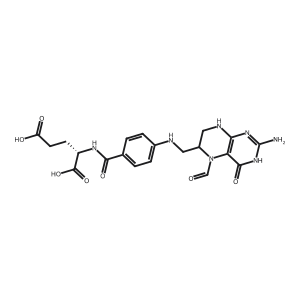
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Reduce methotrexate toxicity (impaired MTX elimination) | Adults | 10 mg/m² (up to 25 mg) q6h | 10 mg/m² (up to 25 mg) q6h until MTX <0.01 µM | 25 mg q6h (above this, use parenteral) |
| Folic acid antagonist / DHFR inhibitor overdose | Adults | 5–15 mg QD | 5–15 mg QD | 15 mg QD |
| FOLR1-CFTD (cerebral folate transport deficiency) | <40 kg | 1–2 mg/kg/day | up to 8.5 mg/kg/day | 8.5 mg/kg/day |
| FOLR1-CFTD | ≥40 kg | 1–2 mg/kg/day | up to 330 mg/day | 330 mg/day |
Renal Undefined
Hepatic Undefined
For MTX rescue, doses >25 mg q6h require switch to injectable leucovorin.
Instructions
- Oral only; with or without food.
- May crush and mix with food/liquid; give immediately after mixing.
- MTX rescue: give within 24 hr of MTX / ASAP after antagonist overdose; maintain IV fluids 3 L/day and alkalinize urine to pH ≥7.0.
- FOLR1-CFTD: total daily dose once daily or divided up to 6x/day; single doses ≤25 mg preferred, do not exceed 75 mg as a single dose.
Available strengths
- tab 5, 10, 15, 25 mg
- sol 100 mg/10 mL
- sol 350 mg/35 mL
- sol 50 mg/5 mL
- sol 500 mg/50 mL
- inj 50, 100, 200, 350, 500 mg
Contraindications
- Hypersensitivity to leucovorin, levoleucovorin, or folic acid — severe reaction (antagonist/DHFR toxicity indication) or any reaction (FOLR1-CFTD); anaphylaxis reported
Cautions
- Hypersensitivity/anaphylactic reactions — withhold or discontinue based on severity
Adverse reactions
- Pruritus, rash, urticaria
- Dyspnea
- Rigors, temperature change
Pregnancy No drug-associated risk identified for intermittent use (antagonist/DHFR toxicity); concomitant chemotherapy may cause fetal harm.
Lactation No data on presence in human milk.
Cost
Generic entry1982
NO BOXED WARNINGS
Principal riskRescue must start on time or it is useless
Classes and tags
Clinical profile
Legacy pregnancy categoryUnknown / historical label unavailable
Defining liabilityGenerally tolerated at therapeutic doses; clinically important risks are agent-specific and increase with interactions or organ impairment.