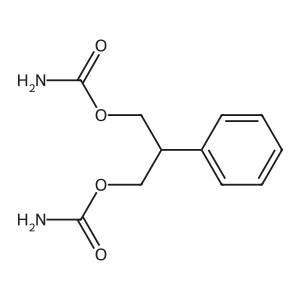
Felbamate
FELBATOL
Pronunciation: fel-BAM-ayt
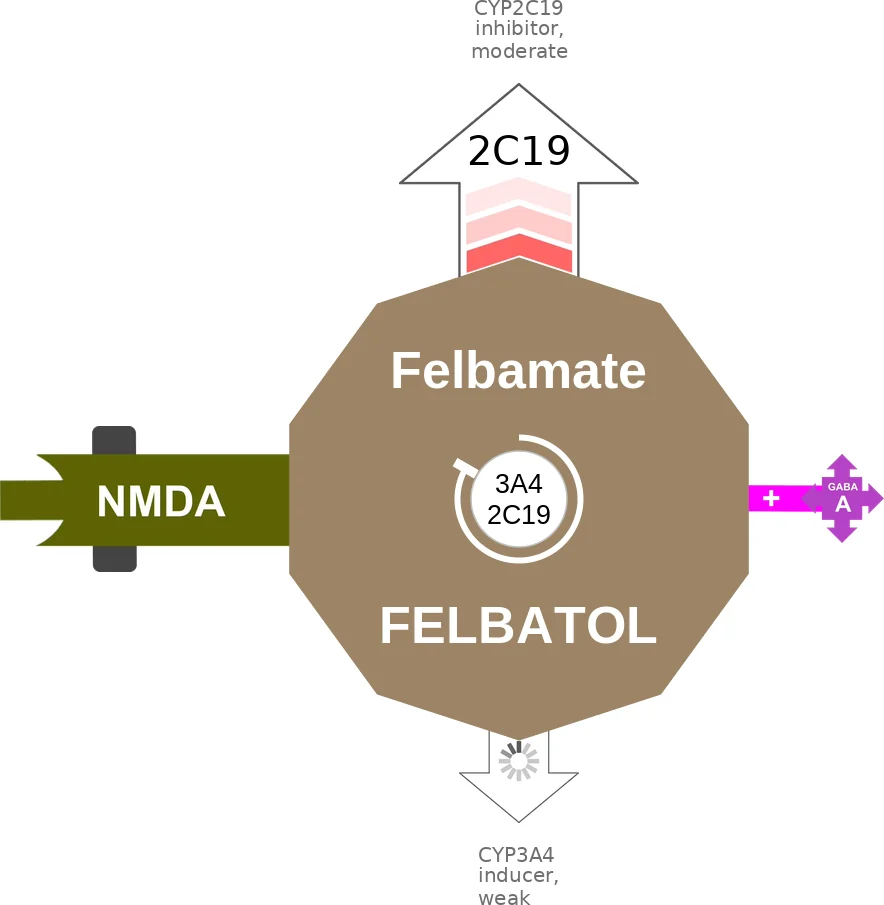

“Fell bat / Fell bam!”
Risk of hepatic failure (very rare)
Risk of aplastic anemia (very rare)
What it isNMDA antagonist (proposed kynurenic-acid-like glycine-site action) and GABA-A positive modulator; refractory Lennox–Gastaut and focal seizures.
Why this oneIts broad efficacy in Lennox-Gastaut can justify use after safer multidrug regimens fail.
What limits itAplastic anemia and hepatic failure demand consent monitoring; it raises phenytoin and valproate.
FDA-approved for
- refractory seizures (1993)
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Epilepsy, monotherapy | Adults ≥14 yr | 1200 mg/day ÷ TID–QID | 2400 mg/day, then 3600 mg/day if indicated | 3600 mg/day |
| Epilepsy, adjunctive | Adults ≥14 yr | 1200 mg/day ÷ TID–QID | up to 3600 mg/day | 3600 mg/day |
| Lennox-Gastaut syndrome, adjunctive | Children 2–14 yr | 15 mg/kg/day ÷ TID–QID | up to 45 mg/kg/day | 45 mg/kg/day (≤3600 mg/day) |
Titration Monotherapy: ↑600 mg every 2 wk. Adjunctive: ↑1200 mg/day (adults) or 15 mg/kg/day (children) at weekly intervals
Renal Use with caution; reduce starting and maintenance doses by one-half
Hepatic Contraindicated in hepatic dysfunction; initiate only in patients without active liver disease and with normal baseline transaminases
Instructions
- When adding or substituting felbamate, reduce concomitant AEDs by 20–33% to control plasma levels and minimize side effects
- Give in divided doses three or four times daily
- Monitor AST/ALT at baseline and periodically; discontinue if AST or ALT ≥2x ULN or if signs of liver failure
- Discontinue if any evidence of bone marrow depression
Available strengths
- tab 400, 600 mg
- susp 600 mg/5 mL
Contraindications
- History of any blood dyscrasia
- History of hepatic dysfunction
Cautions
- Aplastic anemia — consider hematologic consultation; discontinue if bone marrow depression occurs
- Acute hepatic failure — monitor transaminases; do not prescribe with prior hepatic dysfunction; do not re-treat after hepatocellular injury
Adverse reactions
- Anorexia
- Vomiting
- Insomnia
- Nausea
- Headache
- Dizziness (adjunctive)
- Somnolence (adjunctive)
Pregnancy Undefined
Lactation Undefined
Cost
Generic entry2011
⚠ BOXED WARNINGS
- Aplastic anemia
- Hepatic failure
Classes and tags
Clinical profile
Legacy pregnancy categoryC
Defining liabilityAplastic anemia and acute hepatic failure restrict use to severe refractory epilepsy.
Open Felbamate in the interactive console ↗
Memory aids: interaction avatars
