Eltrombopag
PROMACTA
Pronunciation: el-TROM-boe-pag (proe-MAK-ta)
What it isOral thrombopoietin-receptor agonist stimulating megakaryocytes; chronic immune thrombocytopenia and severe aplastic anemia.
Why this oneUnlike injectable TPO agonists it is a tablet, but it uniquely chelates dietary cations and complicates meal timing.
What limits itMonitor liver tests; thrombosis and cataracts occur. Separate it from antacids, dairy and mineral supplements.
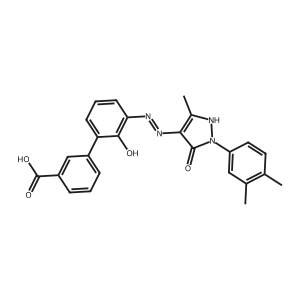
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Persistent or chronic immune thrombocytopenia (ITP) | Adults | 36 mg QD (18 mg QD if East-/Southeast-Asian ancestry OR hepatic impairment Child-Pugh A–C; 9 mg QD if both) | Lowest dose maintaining platelets ≥50×10⁹/L | 54 mg/day |
| Persistent or chronic ITP | Peds ≥6 yr (must swallow tablets whole) | 36 mg QD (18 mg QD if East-/Southeast-Asian ancestry or hepatic impairment; 9 mg QD if both) | Lowest dose maintaining platelets ≥50×10⁹/L | 54 mg/day |
| Chronic hepatitis C-associated thrombocytopenia (to enable interferon/ribavirin therapy) | Adults | 18 mg QD | Adjust by 18 mg q2wk to platelet count needed to start/maintain antiviral therapy | 72 mg/day |
| Refractory severe aplastic anemia | Adults | 36 mg QD (18 mg QD if East-/Southeast-Asian ancestry or hepatic impairment Child-Pugh A–C) | Adjust in 36-mg increments q2wk to platelets ≥50×10⁹/L; response may take up to 16 wk | 108 mg/day |
Titration Wait at least 2 weeks on a dose before increasing (all indications); ITP with hepatic impairment: wait 3 weeks after start or any increase
Renal Undefined
Hepatic ITP and severe aplastic anemia: reduce initial dose to 18 mg QD for Child-Pugh A–C (9 mg QD if also East-/Southeast-Asian ancestry with ITP); chronic hepatitis C: no adjustment
Do not administer more than one dose within any 24-hour period; stop if platelets >400×10⁹/L (see label tables for restart at reduced dose)
Instructions
- NOT substitutable milligram-per-milligram with other eltrombopag products
- Take without a meal or with a low-calcium meal (≤50 mg)
- Take ≥2 h before or 4 h after polyvalent cations (antacids; calcium-rich foods; iron/calcium/aluminum/magnesium/selenium/zinc supplements)
- Swallow tablets whole; do not split, chew, or crush
- Do not use to normalize platelet counts; use lowest effective dose
- ITP: discontinue if platelets do not reach level sufficient to avoid clinically important bleeding after 4 wk at 54 mg/day; monitor CBC weekly until stable, then monthly, and weekly ×4 wk after stopping
- Severe aplastic anemia: discontinue if no hematologic response after 16 wk; consider discontinuing for new cytogenetic abnormalities
- Hepatitis C: discontinue when antiviral therapy is discontinued
- Monitor ALT/AST/bilirubin before start, q2wk during titration, then monthly
- Baseline ocular exam, then monitor regularly for cataracts
Available strengths
- tab 9, 12.5, 18, 25, 36, 50, 54, 75 mg
- susp 12.5, 25 mg
Cautions
- Hepatotoxicity (boxed): monitor liver tests; discontinue for ALT ≥3×ULN (or ≥3× baseline) that is progressive, persistent ≥4 wk, with increased direct bilirubin, or with symptoms/decompensation
- Hepatic decompensation in chronic hepatitis C when combined with interferon and ribavirin (boxed) — higher risk if albumin <3.5 g/dL or MELD ≥10
- Increased risk of death and progression to AML in MDS — not for use in MDS
- Thrombotic/thromboembolic complications (incl. portal vein thrombosis in chronic liver disease); do not normalize platelet counts
- Cataracts: baseline and regular ocular exams
- Laboratory test interference: highly colored — may falsely alter bilirubin, creatinine, and other chemistry results; inform the lab
Adverse reactions
- Anemia, nausea, pyrexia, increased ALT, cough, fatigue, headache, diarrhea (≥20% across indications)
- Hemorrhage after discontinuation (most common serious reaction in ITP)
- Thromboembolic events
Pregnancy Insufficient human data; embryolethality/reduced fetal weight in rats at maternally toxic exposures
Lactation Breastfeeding not recommended during treatment (detected in rat pups)
Cost
Generic entry2025
⚠ BOXED WARNINGS
- Hepatic decompensation in patients with chronic hepatitis C
- Hepatotoxicity
Principal riskBoxed warning: risk of hepatic decompensation in chronic hepatitis C patients and risk of hepatotoxicity.