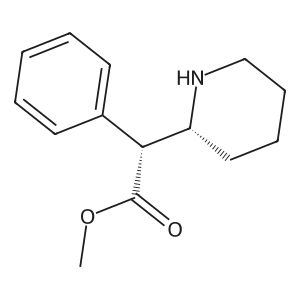
Dexmethylphenidate
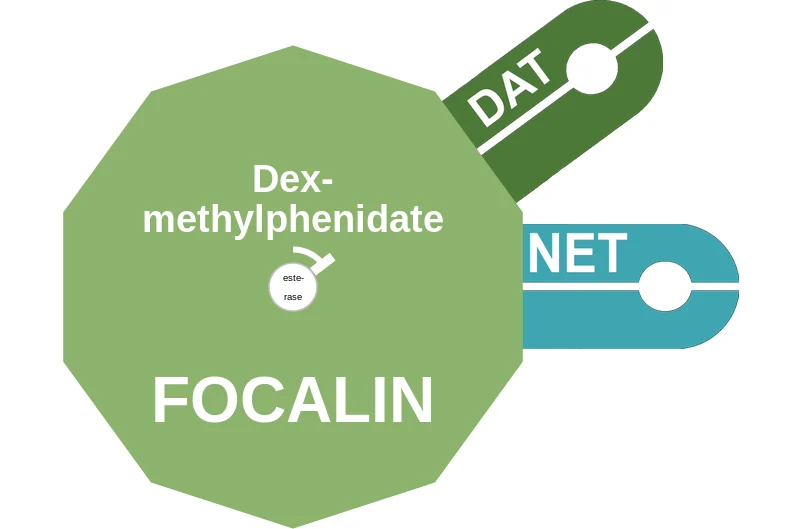
FOCALIN
Pronunciation: dex-meth-il-FEN-i-dayt
“A star is Sir”
Ball and chain" must be clipped
Scantron → methylphenidate product
What it isActive d-enantiomer inhibiting dopamine and norepinephrine reuptake; ADHD.
Why it mattersIt removes the inactive l-enantiomer, allowing a lower milligram burden than racemic methylphenidate.
What it changesAppetite suppression, insomnia, and growth deceleration can limit use. Schedule II; monitor blood pressure and misuse.
FDA-approved for
- ADHD (2001)
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| ADHD — patients new to methylphenidate (or on other stimulants) | Peds ≥6 yr (label dosing text addresses pediatric patients) | 2.5 mg BID (5 mg/day), with or without food | Individualized; titrate weekly 2.5–5 mg | 20 mg/day (10 mg BID) |
| ADHD — patients currently on racemic methylphenidate | Peds (per label dosing text) | Half the current total daily methylphenidate dose | Individualized | 20 mg/day (10 mg BID) |
Titration Weekly (2.5–5 mg increments)
Renal Undefined
Hepatic Undefined
Instructions
- BID, doses at least 4 hours apart, with or without food
- Reduce dose or discontinue if paradoxical aggravation of symptoms or adverse reactions
- Discontinue if no improvement after appropriate dose adjustment over 1 month
- Pretreatment: cardiac history/exam and screen for tics/Tourette's and family history
Available strengths
- tab 2.5, 5, 10 mg
- ER cap 5, 10, 15, 20, 25, 30, 35, 40 mg
Contraindications
- Concomitant MAOI treatment, or within 14 days of stopping an MAOI (hypertensive crisis risk)
Cautions
- Avoid in serious cardiac disease; increases BP and heart rate — monitor
- Psychiatric adverse reactions (psychosis/mania); priapism
- Peripheral vasculopathy incl. Raynaud's
- Long-term growth suppression in peds — monitor growth; interrupt if not growing/gaining as expected
- Acute angle-closure glaucoma / increased IOP
- Emergence/worsening of tics and Tourette's
Adverse reactions
- Peds (≥5% and 2× placebo): abdominal pain, fever, nausea, anorexia
Pregnancy d-enantiomer of methylphenidate; published methylphenidate data have not identified drug-associated risk of major birth defects/miscarriage; possible CNS-stimulant fetal risks; registry available
Lactation Methylphenidate present in milk (infant dose 0.16–0.7% of maternal weight-adjusted dose); no adverse infant reports; monitor breastfed infant
Cost
| Strength | #/mo | generic $/unit | CostPlus | |
|---|---|---|---|---|
| 2.5 mg | tab | per unit | $0.19/ea | not offered |
| 5 mg | tab | per unit | $0.27/ea | not offered |
| 10 mg | tab | per unit | $0.34/ea | not offered |
Other forms: Dexmethylphenidate XR (FOCALIN XR)
Available combined with: azstarys
Generic entry2007
⚠ BOXED WARNING
- Abuse, misuse and addiction
Classes and tags
Clinical profile
Legacy pregnancy categoryC
Defining liabilityCardiovascular stimulation, appetite suppression, insomnia, misuse and stimulant-induced psychosis.