Centanafadine
SIMTRIYO
Pronunciation: sen-tan-AF-a-deen (sim-TREE-yoe)
“Sim trio’s Scent antenna fading”
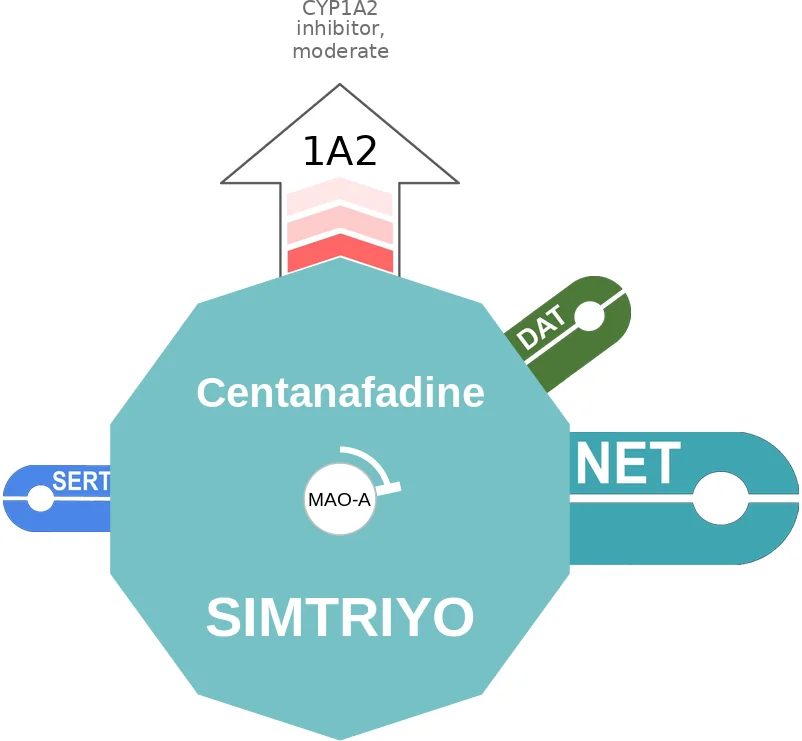
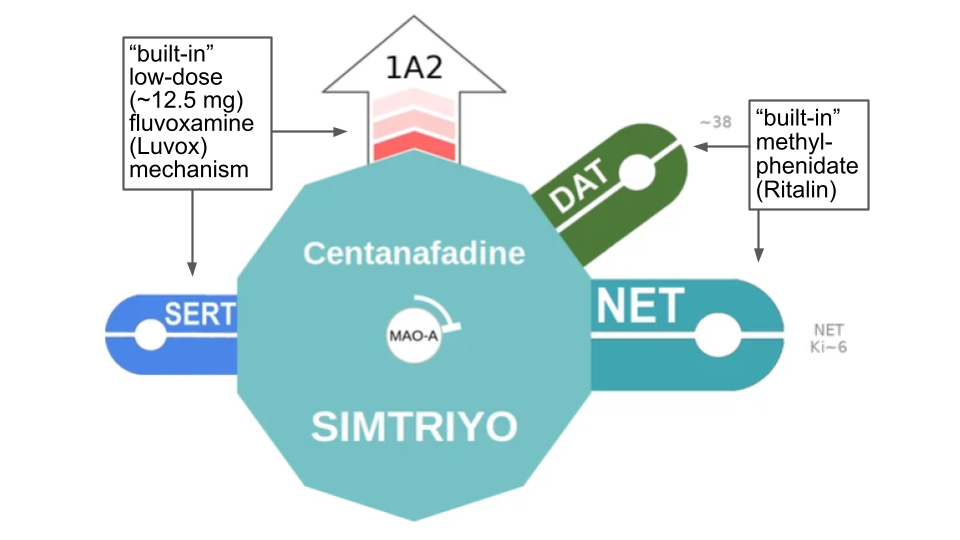
NDSRI: blocks norepinephrine, dopamine, and serotonin reuptake
NDSRI: NET = norepinephrine transporter; DAT = dopamine transporter; SERT = serotonin transporter
What it isNorepinephrine, dopamine, and serotonin reuptake inhibitor; ADHD.
Why this oneUnlike stimulants and atomoxetine, it combines all three monoamine-reuptake mechanisms in one ADHD drug.
What limits itPediatric suicidal ideation and abuse or misuse carry boxed warnings; MAO inhibitors are contraindicated.
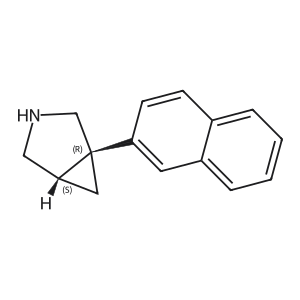
FDA-approved for
- ADHD (adults and children 6 years and older weighing at least 20 kg) (2026)
Available strengths
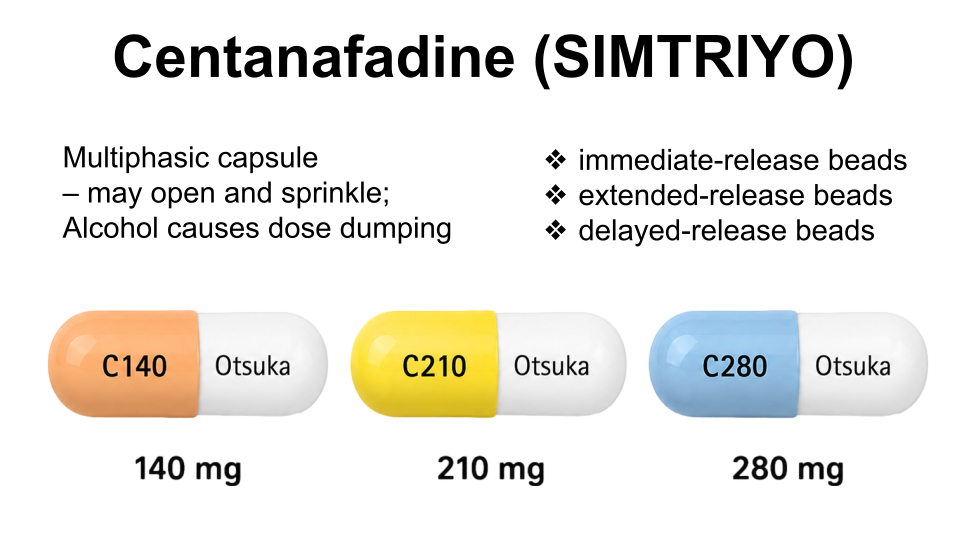
- ER cap 140, 210, 280 mg
⚠ BOXED WARNINGS
- Suicidal ideation and behavior in pediatric patients
- Abuse, misuse and addiction
What it is
First FDA-approved norepinephrine–dopamine–serotonin reuptake inhibitor (NDSRI).
- FDA classifies it as a CNS stimulant; human abuse potential is clinically meaningful
- No head-to-head data, but it appears less effective than methylphenidate or amphetamine
- Awkward liabilities: pediatric suicidality, rash, interactions
- Controlled substance — DEA schedule TBD
Multiphasic capsule — may open and sprinkle
- immediate-release beads
- extended-release beads
- delayed-release beads
Boxed warning · suicidality
BOXED WARNING — Suicidal Ideation and Behavior in Pediatric Patients
6-week study, ages 6–12, suicide attempts
- centanafadine: 2 / 304 patients (0.7%)
- placebo: 0 / 153
Long-term pediatric study
- 4 / 620 (0.6%) discontinued for suicidal ideation
Boxed warning · abuse
BOXED WARNING — Abuse, Misuse, and Addiction
- Positive drug-liking
- Amphetamine-like drug-liking scores at high dose
- No withdrawal effects noted
Approved use and dosing
FDA-approved for ADHD in
- adults
- children and adolescents ≥ 6 yr
Not recommended
- age < 6 yr, or weight < 20 kg
Dosing · once every morning, with or without food
| group | dose | note |
|---|---|---|
| Adults | start 210 mg | max 280 mg, no added benefit |
| Ages 13–17 | target 280 mg | higher than adult; 140 mg ineffective |
| Ages 6–12, 20–<35 kg | 140 mg | |
| Ages 6–12, 35–50 kg | 210 mg | |
| Ages 6–12, > 50 kg | 280 mg |
Adverse effects · ages 6–12
- Rash ~9% in children, 4% in adults
- Decreased appetite ~8% — children under 6 had disproportionate weight suppression
- Nausea 3–10%
- Height reduction by z-score in ~16% of participants ages 6–12; minimal in adolescents
- All other side effects of methylphenidate
Rash, and alcohol
Rash
- The most consistent adverse effect leading to discontinuation
- Angioedema, anaphylaxis and other serious hypersensitivity reactions occurred
- The 210 mg capsule contains tartrazine, which may provoke allergic-type reactions, particularly in aspirin-sensitive patients
Alcohol — dose dumping
- Avoid alcohol for at least 2 hours after a dose: alcohol can release the extended-release fraction all at once
Kinetic interactions
- Substrate of MAO-A
- Mostly urinary excretion
- Moderate CYP1A2 inHibitor
As a perpetrator
caffeine~2xclozapine~2x
Centanafadine against the stimulants
| Amphetamines | Methylphenidates | Centanafadine (SIMTRIYO) | |
|---|---|---|---|
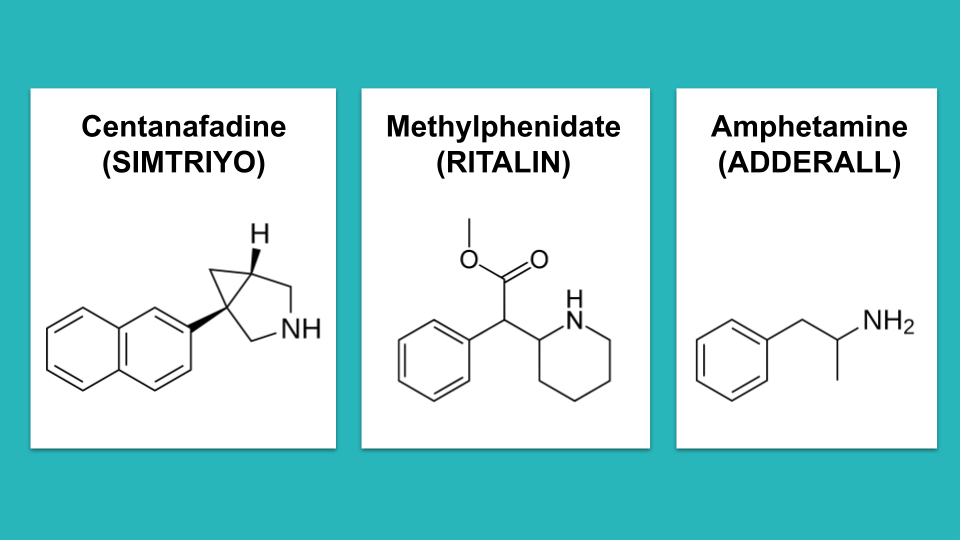
| Core mechanism | DAT/NET releaser | DAT/NET reuptake blocker | NET > DAT ≈ SERT reuptake blocker |
| Examples | Adderall, Dexedrine, Vyvanse | Ritalin, Concerta, Focalin | sole NDSRI class member |
| Youth efficacy | very large, ≈1.02 | ≈0.78, large | ≈0.40, modest |
| Adult efficacy | large, ≈0.79 | ≈0.49, medium | ≈0.24–0.40, small |
| Limiting effects | appetite loss, insomnia, irritability, anxiety, dry mouth, tachycardia | similar, less harsh | like methylphenidate plus rash and suicidality |
| Weight and growth | often greatest appetite suppression | less harsh than amphetamines | not demonstrably gentler than methylphenidates |
| Psychosis / mania | higher risk than methylphenidate | class warning, lower observed risk | same class warning; comparative risk unknown, exposure limited |
| Suicidality | no warning, no increased risk shown | no warning | BOXED WARNING — suicide attempts occurred |
| Hypersensitivity | not a class liability | not a class liability | rash 8–9% pediatric, 4% adult; rare angioedema/anaphylaxis |
| Abuse potential | high · BOXED WARNING | less than amphetamines · BOXED WARNING | like methylphenidate · BOXED WARNING |
| DEA schedule | II | II | likely II, to be announced |
| PK interactions | urinary alkalinization ↑ exposure; minor CYP2D6 substrate | none | moderate CYP1A2 inHibitor — ↑ caffeine 2x |
| Access and cost | numerous inexpensive generics | numerous inexpensive generics | brand only |
Classes and tags
Clinical profile
Serotonin and MAOI
Provisional washout figures
Evidence confidenceModerate
Open Centanafadine in the interactive console ↗
Memory aids: interaction avatars
