Aliskiren
TEKTURNA
Pronunciation: a-lis-KYE-ren
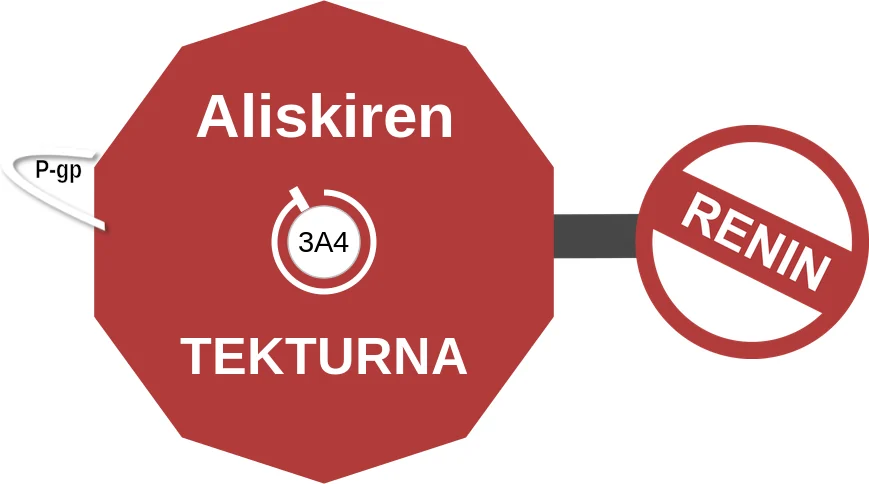

“Tech Turner Alaskas renin”
Tina Turner / Alaska as a verb
Renin clipping angiotensinogen to make angiotensin I
What it isDirect renin inhibitor suppressing the first step of the RAAS cascade; hypertension.
Why this oneIt is mechanistically unique but has no practical outcome advantage over ACE inhibitors or ARBs.
What limits itDo not combine with an ACE inhibitor or ARB in diabetes or renal impairment; hyperkalemia, kidney injury, and fetal toxicity follow.
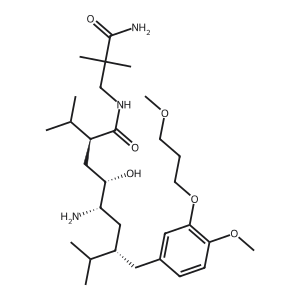
FDA-approved for
- hypertension (2007)
FDA label
Read the full label on DailyMed ↗
| FDA dosing | Population | Start | Target | Max |
|---|---|---|---|---|
| Hypertension | Adults & peds ≥6 yr weighing ≥50 kg | 150 mg QD | Up to 300 mg QD if not controlled | 300 mg QD |
Titration Most of the antihypertensive effect (85-90%) is attained by 2 weeks; assess before increasing dose
Renal Safety/effectiveness not established in severe impairment (CrCl <30 mL/min)
Hepatic Undefined
Instructions
- Take once daily with a consistent pattern regarding meals; avoid high-fat meals (substantially reduce absorption)
- Discontinue as soon as pregnancy is detected
- Correct volume and/or salt depletion before starting, or start under close supervision
Available strengths
- tab 150, 300 mg
Contraindications
- Concomitant use with ARBs or ACE inhibitors in patients with diabetes
- Pediatric patients less than 2 years of age
Cautions
- Anaphylactic reactions and head/neck angioedema — discontinue and do not readminister
- Hypotension in volume/salt-depleted patients
- Impaired renal function/acute renal failure — monitor serum creatinine
- Hyperkalemia — monitor serum potassium; higher risk with ACEI/ARB, NSAIDs, K-sparing agents
- Avoid combined use with ACEI/ARB, particularly if CrCl <60 mL/min
- Avoid concomitant cyclosporine or itraconazole (increase aliskiren levels)
Adverse reactions
- Diarrhea (dose-related), cough, rash, elevated uric acid/gout
Pregnancy Can cause fetal harm; RAAS-acting drugs in 2nd/3rd trimesters reduce fetal renal function and increase morbidity/death. Discontinue when pregnancy is detected.
Lactation Breastfeeding not recommended (potential hypotension, hyperkalemia, and renal impairment in the infant).
Cost
Generic entry2019
⚠ BOXED WARNING
- Fetal toxicity
Classes and tags
Clinical profile
Legacy pregnancy categoryD
Defining liabilityGenerally tolerated at therapeutic doses; clinically important risks are agent-specific and increase with interactions or organ impairment.
Open Aliskiren in the interactive console ↗
Memory aids: interaction avatars
